Capture pocket depths, bleeding on probing, diagnosis, treatment plan, and provider signature in a single, mobile-friendly SOAP note. The template is ready to copy and paste, formatted for quick entry by dental hygienists, assistants, and students. All required periodontal charting fields and a concise signature line are included, enabling immediate use during any periodontal visit.
Initial Periodontal Evaluations
Non-smoker, First Periodontal Evaluation
SOAP note
SSubjective
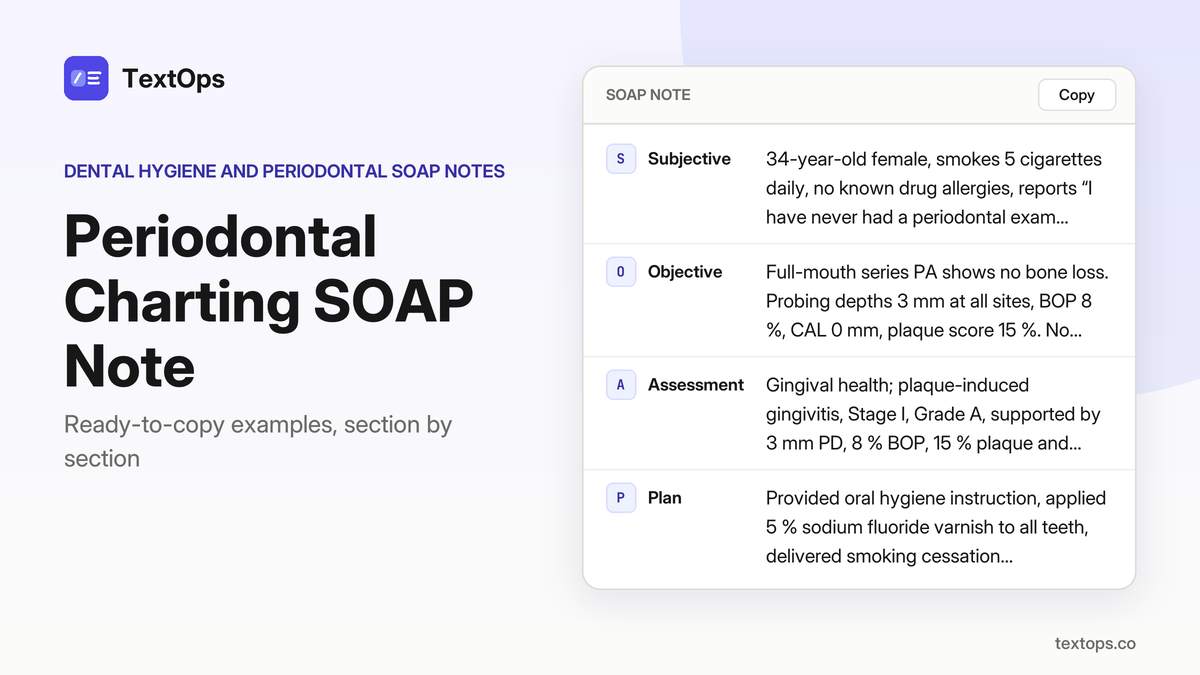
34-year-old female, smokes 5 cigarettes daily, no known drug allergies, reports “I have never had a periodontal exam before.”
OObjective
Full-mouth series PA shows no bone loss. Probing depths 3 mm at all sites, BOP 8 %, CAL 0 mm, plaque score 15 %. No extraoral or intraoral abnormalities noted.
AAssessment
Gingival health; plaque-induced gingivitis, Stage I, Grade A, supported by 3 mm PD, 8 % BOP, 15 % plaque and absence of bone loss.
PPlan
Provided oral hygiene instruction, applied 5 % sodium fluoride varnish to all teeth, delivered smoking cessation counseling, and scheduled periodontal maintenance in 6 months. No medications or anesthesia were used.
Diabetic, HbA1c 8.2%, Stage II Periodontitis
SOAP note
SSubjective
36-year-old female, type 2 diabetes on metformin, asthma, NKDA, reports “I feel my gums bleed when I brush.”
OObjective
Probing depths 4 mm at #15-#17, BOP 25 %, CAL 2 mm at #15-#17, plaque score 35 %; full-mouth series shows 1–2 mm bone loss around #15-#17; HbA1c 8.2 %; no anesthesia used.
AAssessment
Stage II Periodontitis, Grade C, supported by 4 mm pockets, 25 % BOP, 1–2 mm bone loss and HbA1c > 7.0 %.
PPlan
Scaling and root planing quadrant 2, oral hygiene instruction, fluoride varnish 5 % sodium fluoride on all teeth, referral to periodontist for maintenance schedule, advise tighter glycemic control.
Gum Bleeding, 5-Year Recall
SOAP note
SSubjective
64-year-old male, seasonal allergies, NKDA, reports “I come for my cleaning.” HPI: routine visit, no pain or swelling.
OObjective
Extraoral normal. Intraoral: plaque score 20%; probing depths 3 mm at all sites; BOP 12%; CAL 0 mm; no suppuration. Radiograph: full-mouth series shows no bone loss.
AAssessment
Gingival health; plaque-induced gingivitis, Stage I, Grade A—supported by probing depths ≤3 mm, BOP 12 %, CAL 0 mm, and no radiographic bone loss.
PPlan
Prophylaxis performed: scaling and polishing, fluoride varnish 5 % sodium fluoride applied to all teeth, oral hygiene instruction given. No medications prescribed. Next cleaning scheduled in 6 months.
Gingival Recession, Tooth 24
SOAP note
SSubjective
43-year-old male, NKDA, daily low-dose aspirin; CC: “I have a sunken gum line on my upper left canine”; HPI: no pain, no bleeding, no swelling; PMH: aspirin, no other systemic disease.
OObjective
Extraoral: WNL; Intraoral: plaque score 18%; Periodontal: probing depth 3 mm at #11, BOP 0%, CAL 1 mm (recession 1 mm); Radiographic: PA of #11 shows no bone loss; Tests: none.
AAssessment
Gingival recession, Stage I, Grade A – supported by 1 mm recession, 3 mm probing depth, 0 % BOP, and absence of bone loss.
PPlan
Provided oral hygiene instruction; applied 5 % sodium fluoride varnish to all teeth; advised interdental brush for #11; no anesthesia or drugs used; scheduled periodontal maintenance in 3 months.
Diabetic, HbA1c 7.8%, Stage I Periodontitis
SOAP note
SSubjective
67-year-old female, type 2 diabetes on metformin, allergic to penicillin (rash); CC: “My gums bleed a lot and I have a bad taste”; HPI: bleeding gums for several weeks, no pain; PMH: diabetes, no other systemic disease; allergy: penicillin rash.
OObjective
Extraoral: no swelling or lymphadenopathy. Intraoral: plaque score 30 %; probing depths 3 mm at all sites; BOP 20 %; CAL 1 mm at several sites; radiograph: 1–2 mm bone loss around #11-#13; HbA1c 7.8 %.
AAssessment
Stage I Periodontitis, Grade C (HbA1c > 7.0 %) supported by probing depths ≤3 mm, BOP 20 %, CAL 1 mm, and 1–2 mm bone loss.
PPlan
Scaling and root planing quadrant 1 (upper left) performed; fluoride varnish 5 % sodium fluoride applied to all teeth; oral hygiene instruction given; referred to periodontist for maintenance; advised tighter glycemic control; no drugs prescribed.
Routine Recall & Prophylaxis
Smoker, 3-Month Maintenance Recall
SOAP note
SSubjective
39-year-old female, smoker 5 cigarettes/day, type 2 diabetes on metformin, NKDA; CC: “Here for my cleaning”; HPI: routine recall, no pain or swelling; PMH: diabetes, smoking; meds: metformin; allergies: NKDA.
OObjective
Plaque index 25%; light supragingival calculus on all teeth; BOP 5%; probing depths 2 mm all sites; no recession, no mobility, no suppuration, no caries, no periodontal abscess; extraoral and intraoral otherwise normal.
AAssessment
Gingival health; plaque-induced gingivitis, Stage I, Grade C (smoking); findings support diagnosis: mild plaque, minimal BOP, shallow PD, no attachment loss.
PPlan
Full-mouth prophylaxis performed: supragingival scaling, polishing, oral hygiene instruction; no anesthesia, no drugs; POI: maintain brushing twice daily, interdental cleaning, avoid tobacco; next visit in 3 months for maintenance.
Post-Extraction, Day 2, Lower Molar
SOAP note
SSubjective
73-year-old female, hypothyroidism on levothyroxine, reports “I’m fine, just a little sore” after extraction of tooth #30 on day 2; no pain, no swelling, no trismus, no fever.
OObjective
Extraction site #30 shows mild erythema, no swelling, BOP 0 %, PD 0 mm, no suppuration; overall healing is satisfactory with no signs of infection.
AAssessment
Healing extraction site, no infection.
PPlan
Sutures removed. Oral hygiene instruction provided, emphasizing gentle brushing around the site, use of a soft diet, and rinsing with saline 2–3 times daily. No medication prescribed. Patient advised to return in 4 weeks for routine recall to monitor healing and reinforce oral hygiene.
Orthodontic Patient, 6-Month Retainer Check
SOAP note
SSubjective
54-year-old male, former smoker, NKDA, presents for a routine orthodontic retainer check; he reports “Just checking my retainer” and has no pain or other complaints.
OObjective
The removable retainer is in place, clean, and free of debris; the patient’s oral hygiene is good with a plaque index of 20 %. No carious lesions, no periodontal pockets, and no gingival bleeding were noted. Extraoral and intraoral examinations were otherwise within normal limits.
AAssessment
Gingival health; plaque-induced gingivitis, Stage I, Grade A, confirmed by the plaque index, absence of probing depth changes, and lack of bleeding on probing.
PPlan
The retainer was cleaned and polished; comprehensive oral hygiene instruction was reinforced, emphasizing proper brushing, flossing, and retainer care to maintain plaque control. No medications were prescribed. The patient was advised to return in 6 months for the next routine retainer maintenance visit.
Implant Site, 1-Year Maintenance
SOAP note
SSubjective
45-year-old male, smoker 5 cigarettes a day, NKDA, states “Just a routine check” and reports no pain, swelling, or bleeding.
OObjective
Implant site #30 is probeable with a probing depth of 2 mm and no bleeding on probing. No suppuration is present. Periapical radiograph shows no peri-implant radiolucency and no bone loss. The implant surfaces are free of calculus and the surrounding mucosa is pink, healthy, and non-inflamed. Vital signs were within normal limits and the patient was comfortable throughout the examination.
AAssessment
Implant maintenance, healthy peri-implant tissues, confirmed by PD 2 mm, 0 % BOP, absence of suppuration, and normal radiographic findings.
PPlan
Performed ultrasonic scaling of the implant surface, followed by polishing with a rubber cup and a non-abrasive polishing paste. Reinforced oral hygiene instructions, emphasizing interdental cleaning with a dental floss threader and a soft-bristle brush around the implant. No medications were prescribed. Scheduled next maintenance visit in 6 months.
Post-Fluoride Varnish, 2-Week Follow-up
SOAP note
SSubjective
59-year-old female, controlled hypertension on lisinopril, no known drug allergies, presents for a 2-week follow-up after fluoride varnish application; she reports no pain and says, “Just checking the varnish.”
OObjective
Fluoride varnish on #12-#14 remains intact, no staining observed. Plaque index 15%; no caries, no periodontal disease, no bleeding on probing. Extraoral and intraoral examination normal. No radiographs taken.
AAssessment
Gingival health; plaque-induced gingivitis, Stage I, Grade A, supported by 15 % plaque, absence of bleeding or pockets, and intact varnish.
PPlan
No anesthesia or medication administered. Reinforced oral hygiene instructions, advised avoidance of hard foods for 24 hrs, and scheduled next routine recall in 6 months.
Smoking Cessation, 5-Year Recall
SOAP note
SSubjective
52-year-old female, smoker 5 cigarettes/day, NKDA, CC: “I’m still smoking, but want to quit.” HPI: patient reports continued smoking despite prior attempts, no pain, swelling, or other symptoms; she is motivated to stop but uncertain about strategies.
OObjective
Plaque index 30 %; moderate calculus present on all molars; BOP 10 % of sites; probing depths 3 mm on molars; no gingival recession, mobility, suppuration, caries, or periodontal abscess noted; periodontal tissues appear healthy aside from inflammation.
AAssessment
Gingival health; plaque-induced gingivitis, Stage I, Grade C (smoking).
PPlan
Provided comprehensive smoking-cessation counseling, including brief intervention techniques, discussed risks of continued smoking, and offered referral to a quitline for ongoing support; reinforced oral hygiene instruction with emphasis on daily brushing, interdental cleaning, and chlorhexidine rinses as needed. No pharmacologic agents prescribed. Scheduled next routine recall in 5 years, with interim telephone check-in at 3 months to monitor progress.
Post-Orthodontic, 1-Year Retainer Check
SOAP note
SSubjective
20-year-old male, asthma, albuterol PRN, NKDA, chief complaint: “Here for my cleaning and retainer check.”
OObjective
Plaque index 15%; light calculus; bleeding on probing 5% of sites; probing depth 2 mm at all sites; no recession; extraoral and intraoral otherwise normal; no radiographs taken; no tests performed.
AAssessment
Gingival health; plaque-induced gingivitis, Stage I, Grade A, supported by 5% BOP, 2 mm PD, light calculus and 15% plaque index.
PPlan
Prophylaxis performed with ultrasonic scaling and hand polishing; retainer adjusted for proper fit; flossing technique reinforced; patient advised to maintain daily flossing and return in 6 months for routine recall.
Gum Bleeding, 2-Week Recall
SOAP note
SSubjective
51-year-old female patient, seasonal allergies, NKDA, presents for a 2-week recall with the chief complaint, “I noticed some bleeding when brushing,” and reports no pain or swelling.
OObjective
Extraoral exam is unremarkable; intraoral examination shows plaque accumulation of 30 % and moderate supragingival calculus; probing depth is 3 mm at all sites; bleeding on probing is present at 25 % of sites; no suppuration or mobility noted; no anesthesia was required for the procedure.
AAssessment
Diagnosis is plaque-induced gingivitis, Stage I, Grade A, evidenced by 25 % BOP, uniform 3 mm PD, and the presence of plaque and calculus without attachment loss or pocket formation.
PPlan
Scaling and polishing were performed as prophylaxis; oral hygiene instruction reinforced proper brushing technique, interdental cleaning, and the importance of regular recalls; no medications prescribed; patient advised to return in 4 weeks for maintenance.
Gingival Recession, 3-Month Recall
SOAP note
SSubjective
28-year-old male, NKDA, takes low-dose aspirin; CC: “My gums look lower around my front teeth.” HPI: reports mild gingival recession noticed over past month.
OObjective
Tooth #12 mesial recession 1 mm; #13 buccal recession 1.5 mm; CAL 3 mm on both; PD 3 mm; BOP 10%; no systemic signs; no anesthesia used.
AAssessment
Gingival recession, Stage I, Grade A, supported by 1–1.5 mm recession, 3 mm CAL, 10 % BOP, PD 3 mm.
PPlan
Provided oral hygiene instruction, applied 5 % fluoride varnish to #12 and #13; advised use of soft-bristle toothbrush; no medication prescribed; schedule next recall in 3 months.
Post-SRP, 12-Month Maintenance
SOAP note
SSubjective
70-year-old male, no significant medical history, chief complaint: “I’m here for maintenance after my cleaning.”
OObjective
Probing depth 3 mm at all sites on #30-#31; BOP 5 %; CAL 4 mm; no suppuration; extraoral and intraoral findings within normal limits; no anesthesia used.
AAssessment
Periodontitis, Stage II, Grade A (post-SRP) – supported by 3 mm probing depths, 5 % BOP, and 4 mm CAL.
PPlan
Prophylaxis performed; oral hygiene instruction reinforced; chlorhexidine 0.12 % rinse 15 mL for 30 sec, twice daily for 7 days; next maintenance visit scheduled in 3 months.
Gum Bleeding, 6-Month Recall
SOAP note
SSubjective
80-year-old male, type 2 diabetes on metformin, NKDA, reports “My gums bleed a lot when I floss.”
OObjective
Plaque 35 %; heavy calculus; BOP 30 % of sites; PD 4 mm all sites; CAL 5 mm; no suppuration; no anesthesia used.
AAssessment
Periodontitis, Stage III, Grade C (diabetes), supported by heavy calculus, 30 % BOP, 4-mm pockets and 5-mm CAL.
PPlan
Prophylaxis performed; oral hygiene instruction reinforced; chlorhexidine 0.12 % rinse 15 mL for 30 s, twice daily for 7 days; patient advised to return for periodontal evaluation and possible SRP.
Post-Orthodontic, 6-Month Retainer Check
SOAP note
SSubjective
38-year-old female, hypothyroidism on levothyroxine, allergic to penicillin (rash), chief complaint: “Checking my retainer after orthodontics.” HPI: patient reports routine check-up, no pain or discomfort. PMH: hypothyroidism, no other systemic disease.
OObjective
Extraoral: normal. Intraoral: plaque 20 %; light calculus; BOP 5 %; probing depth 2 mm; no recession. Periodontal chart: gingival health, plaque-induced gingivitis, Stage I, Grade A. Radiographs: none taken.
AAssessment
Plaque-induced gingivitis, Stage I, Grade A, supported by 20 % plaque, light calculus, 5 % BOP, 2 mm PD.
PPlan
Prophylaxis performed with ultrasonic scaler and hand instruments; retainer adjusted for fit; oral hygiene instruction reinforced; no drugs prescribed. Patient advised to maintain daily brushing and flossing, return in 6 months for routine recall.
Maintenance Scaling (Higher BOP)
Post-SRP, 4-Week Re-evaluation
SOAP note
SSubjective
35-year-old male, former smoker, NKDA, reports “Here for my follow-up after the deep cleaning.” He has no systemic signs and is not on medication.
OObjective
PD 4 mm at tooth #30, 3 mm at #31; BOP 30 % of sites; CAL 4 mm at #30, 3 mm at #31; plaque score 15 %; no suppuration; radiograph shows no new bone loss.
AAssessment
Periodontitis, Stage II, Grade A (post-SRP) – supported by residual pockets >4 mm, high BOP, and maintained CAL.
PPlan
Discussed maintenance plan; reinforced oral hygiene instruction; scheduled next periodontal maintenance in 3 months; no anesthesia or drugs administered.
Implant Site, 6-Month Maintenance
SOAP note
SSubjective
22-year-old male, smoker 5 cigarettes/day, NKDA; CC: “Just a routine check of my implant”; HPI: routine maintenance visit, no pain or swelling; PMH: smoking only; no medications; no allergies.
OObjective
Implant probing depth 2 mm; BOP 10 % of sites; no suppuration; radiograph shows peri-implant bone levels stable; plaque score 10 %; extraoral and intraoral otherwise normal.
Cleaned implant surface with ultrasonic scaler; reinforced oral hygiene instructions; no anesthesia or drugs used; next maintenance scheduled in 6 months.
Post-SRP, 6-Month Re-evaluation
SOAP note
SSubjective
68-year-old female, controlled hypertension on lisinopril, no known drug allergies, presents for a 6-month post-SRP evaluation with the statement, “I’m back for my 6-month check after the scaling.”
OObjective
Extraoral normal. Intraoral: probing depths 3 mm at #15, 4 mm at #16; BOP 20 % of sites; CAL 3 mm at #15, 4 mm at #16; plaque score 12 %; radiograph shows no new bone loss; no suppuration.
AAssessment
Periodontitis, Stage II, Grade A (post-SRP) supported by persistent pockets >3 mm, BOP 20 %, and CAL 3–4 mm.
PPlan
No anesthesia used. Continue periodontal maintenance; consider targeted scaling of #16 if PD remains >3 mm. Reinforce oral hygiene instruction; schedule next maintenance visit in 3 months.
46-year-old female patient, NKDA, presents for her scheduled 6-month periodontal recall; she reports that her gums still bleed when brushing or flossing, despite her regular oral hygiene routine.
OObjective
Extraoral exam is unremarkable. Intraoral examination shows generalized gingival inflammation with erythema and occasional spontaneous bleeding. Periodontal charting reveals BOP at 35 % of sites, all probing depths ≤3 mm, with no pockets >4 mm and no suppuration. Plaque accumulation is moderate, plaque score 18 %. Radiographs (PA and BWX) show no bone loss or radiographic changes.
AAssessment
Diagnosis is gingival health; plaque-induced gingivitis, Stage I, Grade A, as evidenced by BOP >10 % and probing depths ≤3 mm without attachment loss.
PPlan
No local anesthesia was required. The patient received comprehensive oral hygiene instruction, including gentle brushing technique, interdental cleaning with a soft-bristle interdental brush, and the recommendation to avoid aggressive brushing of the bleeding sites for 24 hours. She was advised to increase fluoride toothpaste to 5000 ppm twice daily and to use a 0.12 % chlorhexidine rinse 15 mL for 30 seconds twice daily for the next week. No medications were prescribed. A follow-up recall is scheduled in 3 months to reassess periodontal status.
47-year-old male, asthma, NKDA, reports “retainer feels loose and my gums look a bit recessed.” History: no systemic symptoms, no pain.
OObjective
Recession 2 mm at #12, 1.5 mm at #13; BOP 20 % of sites; PD 3 mm; plaque score 14 %; no suppuration; radiograph shows no bone loss; retainer fit acceptable but needs adjustment.
AAssessment
Gingival recession, Stage I, Grade A, supported by 2–1.5 mm recession, BOP 20 %, PD 3 mm, and absence of bone loss.
PPlan
Adjusted retainer, reinforced oral hygiene instructions, discussed free gingival graft if recession exceeds 2 mm, scheduled next retainer check in 3 months.
Post-Procedure Follow-ups
Periodontal Abscess, Tooth 12
SOAP note
SSubjective
30-year-old female with seasonal allergies, NKDA, presents with a sore spot near her upper left first molar; she reports the pain as throbbing and worsening over the past two days, with no fever or swelling beyond the localized area.
OObjective
Clinical examination shows probing depths of 8 mm on both buccal and lingual aspects of tooth #14, with bleeding on probing in 100 % of sites and purulent suppuration at the gingival margin; radiograph demonstrates a periradicular radiolucency extending to the apex of #14. Extraoral and intraoral findings reveal no tooth mobility, no furcation involvement, and no other periodontal pockets; systemic review is negative for trismus, lymphadenopathy, or constitutional symptoms.
AAssessment
Diagnosis is periodontal abscess of tooth #14, confirmed by deep pockets, BOP, suppuration, and radiographic evidence of a periradicular lesion; no mobility or furcation involvement limits the extent of the infection.
PPlan
Incision and drainage of the abscess were performed under local conditions with no anesthesia; comprehensive oral hygiene instruction was provided, and the patient was prescribed chlorhexidine 0.12 % rinse 15 mL twice daily for 7 days. She was advised to return in 3 days for reassessment of healing and to ensure resolution of the abscess.
Periodontal Surgery, Crown Lengthening
SOAP note
SSubjective
27-year-old male, chief complaint: “I need more space for my crown.” No systemic symptoms; takes low-dose aspirin, NKDA.
OObjective
Tooth #16: PD 4 mm mesial and distal; BOP 20%; CAL 6 mm; radiograph shows 3 mm bone loss around #16; no mobility, no furcation involvement.
AAssessment
Crown lengthening indicated for tooth #16, supported by pocket depths, attachment loss, and radiographic bone loss.
PPlan
Incision and flap elevation performed; 3 mm of bone removed coronally; sutured with 5-0 Vicryl. Post-op chlorhexidine 0.12 % rinse prescribed; patient instructed to avoid brushing the flap for 5 days. No drugs given. Follow-up scheduled in 2 weeks for suture removal and healing assessment.
Periodontitis, Stage IV, Complex Case
SOAP note
SSubjective
60-year-old male, no significant medical history, allergic to penicillin (rash); CC: “My gums are still bleeding after cleaning”; HPI: bleeding gums noted after recent cleaning; PMH: none.
OObjective
Extraoral: normal; Intraoral: tooth #30 shows PD 7 mm buccal and lingual, BOP 100%, CAL 9 mm; Radiograph: generalized bone loss 5 mm, 5 teeth lost; no mobility, no furcation involvement; no systemic signs.
AAssessment
Periodontitis, Stage IV, Complex Case, tooth #30, supported by PD ≥ 7 mm, CAL ≥ 9 mm, generalized bone loss, and tooth loss.
PPlan
Re-evaluation of periodontal status; patient advised strict oral hygiene and chlorhexidine 0.12% rinse; referral to periodontist for full-mouth periodontal surgery with regenerative materials; next visit in 4 weeks for surgical planning.
Periodontal Surgery, Graft Placement
SOAP note
SSubjective
42-year-old male, type 2 diabetes on metformin, NKDA, reports “a shallow pocket that keeps getting infected” around tooth #25.
OObjective
PD 6 mm mesial and distal to #25, BOP 80 %, suppuration present; radiograph shows 4 mm bone loss; no mobility, no furcation involvement; extraoral and intraoral otherwise normal.
AAssessment
Periodontal surgery, graft placement on tooth #25, indicated by deep pockets, high BOP, suppuration and radiographic bone loss.
PPlan
Incision and flap elevation, connective tissue graft from palate, sutured with 5-0 Vicryl; prescribed chlorhexidine 0.12 % rinse; instructed to avoid brushing the graft site for 7 days; next visit in 10 days for suture removal and healing assessment.
Periodontal Surgery, Flap Surgery for Bone Loss
SOAP note
SSubjective
41-year-old male, hypothyroidism on levothyroxine, allergic to penicillin (rash); chief complaint: “My lower left second premolar feels loose”; no systemic signs, no medications besides levothyroxine.
OObjective
Extraoral normal; intraoral: tooth #20 shows PD 8 mm buccal and lingual, BOP 100 %, CAL 10 mm, no mobility; radiograph: 5 mm bone loss, Grade III furcation involvement, Glickman grade III; no other findings.
AAssessment
Periodontal surgery, flap surgery for bone loss on tooth #20, supported by deep pockets, full BOP, significant CAL, radiographic bone loss, and Grade III furcation involvement.
PPlan
Incision, flap elevation, debridement of bone defects, bone graft placement, sutured with 5-0 Vicryl; prescribed chlorhexidine 0.12 % rinse, instructed to avoid brushing the flap for 5 days; next visit in 2 weeks for suture removal and healing assessment.
Periodontal Abscess, Tooth 18, Systemic Symptoms
SOAP note
SSubjective
61-year-old male, former smoker, NKDA; CC: “I have a painful swelling on my upper right second molar”; HPI: swelling, pain, malaise, fever 99.4°F, lymphadenopathy, mild trismus; PMH: none significant; meds: none; allergies: NKDA.
Periodontal abscess, tooth #2, with systemic signs of fever, malaise, lymphadenopathy and mild trismus.
PPlan
Incision and drainage performed; oral hygiene instruction given; chlorhexidine 0.12 % rinse 15 mL twice daily for 7 days; prescribed amoxicillin 500 mg qid for 7 days and acetaminophen 500 mg q6h PRN up to 3 days; advised return in 2 days for reassessment.
Post-SRP, 6-Month Re-evaluation, Residual Pockets
SOAP note
SSubjective
63-year-old female, smoker 5 cigarettes/day, NKDA, reports “I still have pockets after my last cleaning.”
OObjective
PD 5 mm at mesial and distal of #30 and #31; BOP 30%; CAL 6 mm; radiograph shows 3 mm residual bone loss; no mobility, no furcation involvement; extraoral and intraoral otherwise unremarkable.
AAssessment
Post-SRP, 6-month re-evaluation, residual pockets on #30, #31 confirmed by PD, BOP, CAL, and radiographic bone loss.
PPlan
Re-evaluation performed; patient instructed on strict oral hygiene, chlorhexidine 0.12% rinse 15 mL twice daily; plan targeted SRP of remaining pockets; next visit in 4 weeks for further SRP.
Complex/Referral Cases
Pregnancy, Third Trimester, Periodontitis
SOAP note
SSubjective
31-year-old female patient, pregnant, controlled hypertension on lisinopril, NKDA. Chief complaint: “I have been bleeding a lot from my gums during brushing.” History: no systemic signs, no medications other than lisinopril.
OObjective
Probing depths: #15 6 mm, #16 5 mm, #17 6 mm; BOP 70 % of sites; CAL: #15 8 mm, #16 7 mm, #17 8 mm; plaque score 45 %; radiograph shows bone loss around #15 and #17; mobility Miller 0.
AAssessment
Periodontitis, Stage III, Grade C, evidenced by PD ≥ 5 mm, CAL ≥ 7 mm, BOP 70 %, and radiographic bone loss.
PPlan
Referred to periodontist for full-mouth scaling and root planing and a periodontal maintenance plan. Discussed strict oral hygiene, possible antibiotic therapy if systemic signs develop. No drugs prescribed today. Next visit: referral appointment with periodontist.
Periodontitis, Stage III, Complex Case
SOAP note
SSubjective
72-year-old male, NKDA, reports “My gums still bleed and I feel a bad taste.” History: no significant medical issues.
OObjective
Extraoral: normal. Intraoral: plaque score 50%. Periodontal: PD 7 mm (#30), 8 mm (#31), 6 mm (#32); BOP 80 % of sites; CAL 9 mm (#30), 10 mm (#31), 8 mm (#32); mobility Miller 1 (#31); furcation Glickman II (#31). Radiograph: advanced bone loss. No systemic signs.
AAssessment
Periodontitis, Stage III, Grade C, supported by deep pockets, high BOP, significant CAL loss, furcation involvement, and mobility.
PPlan
Planned full-mouth SRP with adjunctive local antibiotic therapy; no anesthesia used. Discussed referral to periodontist for possible regenerative surgery. Instructed on intensive oral hygiene and scheduled next periodontal re-evaluation in 4 weeks.
78-year-old female, asthma, NKDA, reports “the implant site has been red and swollen for a week.”
OObjective
Implant K shows PD 6 mm, BOP 60 % of sites, suppuration present; radiograph reveals bone loss around implant K; plaque score 35 %.
AAssessment
Peri-implantitis, Stage II, Grade B, supported by deep pockets, bleeding, suppuration and radiographic bone loss.
PPlan
Performed implant debridement with curettes and ultrasonic scaler; prescribed chlorhexidine 0.12 % rinse 15 mL, 30 s, twice daily for 2 weeks; referred to implant specialist for possible bone graft; next visit in 3 months for maintenance.
Periodontitis, Stage IV, Complex Case, Referral
SOAP note
SSubjective
66-year-old female, seasonal allergies, NKDA, complains “My gums are very painful and I have lost several teeth.”
OObjective
PD: #20 9 mm, #21 10 mm, #22 8 mm, #23 9 mm; BOP 90 % of sites; CAL: #20 12 mm, #21 13 mm, #22 11 mm, #23 12 mm; plaque score 60 %; radiograph shows generalized bone loss with 5 teeth lost; mobility Miller 2 on #21; furcation Glickman III on #22.
AAssessment
Periodontitis, Stage IV, Grade C, supported by deep pockets, high BOP, extensive CAL loss, mobility, furcation involvement, and generalized bone loss.
PPlan
Referred to periodontist for comprehensive therapy including possible extraction, regenerative surgery, and implant placement; discussed potential systemic antibiotics if infection develops.
Pregnancy, Third Trimester, Recurrent Bleeding, Referral
SOAP note
SSubjective
77-year-old pregnant female, on low-dose aspirin, reports “my gums bleed every time I brush and it keeps happening.” Medical history: pregnancy, low-dose aspirin, NKDA. HPI: recurrent bleeding, no pain, no swelling, no systemic symptoms.
OObjective
Extraoral: normal. Intraoral: PD #3 5 mm, #4 6 mm, #5 5 mm; BOP 75 % of sites; CAL #3 7 mm, #4 8 mm, #5 7 mm; plaque score 40 %; radiograph: mild bone loss; mobility Miller 0.
AAssessment
Periodontitis, Stage II, Grade C, supported by PD ≥5 mm, BOP >70 %, CAL ≥7 mm, and radiographic bone loss.
PPlan
Referred to periodontist for full-mouth scaling and root planing. Discussed aspirin use and possible temporary discontinuation under obstetric guidance. No drugs prescribed today. Next visit: periodontal follow-up in 4 weeks.
Pregnancy, Second Trimester, Recurrent Bleeding
SOAP note
SSubjective
65-year-old pregnant female, allergic to penicillin, reports “my gums bleed a lot and I feel a bad taste”; medical history includes pregnancy, no systemic signs.
OObjective
Extraoral normal. Intraoral: PD 6 mm at #12, 5 mm at #13, 6 mm at #14; BOP 70 % of sites; CAL 8 mm at #12, 7 mm at #13, 8 mm at #14; plaque score 45 %; radiograph shows moderate bone loss; mobility Miller 0.
AAssessment
Periodontitis, Stage II, Grade C, supported by PD ≥ 5 mm, CAL ≥ 7 mm, BOP 70 %, moderate bone loss.
PPlan
Referred to periodontist for full-mouth SRP; discussed antibiotic alternatives safe in pregnancy; no drugs prescribed today; instructed to maintain oral hygiene and return for follow-up after specialist treatment.
Medical/High-Risk Patients
Pregnant, Second Trimester, Gingivitis
SOAP note
SSubjective
23-year-old female, pregnant, type 2 diabetes on metformin, NKDA; CC: “Here for my cleaning, my gums bleed a bit.” HPI: mild bleeding with routine brushing, no pain, no swelling, no systemic symptoms.
OObjective
BOP 15 % of sites, PD max 3 mm, no CAL, plaque index 25 %, no suppuration, no mobility, no furcation involvement; extraoral normal.
AAssessment
Gingival health; plaque-induced gingivitis, Stage I, Grade A – supported by BOP 15 %, PD ≤3 mm, plaque 25 %.
PPlan
Scaling and root planing of all teeth, polishing, OHI, fluoride varnish 5 % sodium fluoride applied to all teeth; no anesthesia, no drugs; instructed to maintain oral hygiene, avoid irritants, and return for routine prophylaxis in 3 months.
Pregnancy, First Trimester, Mild Gingivitis
SOAP note
SSubjective
58-year-old female, pregnant, hypothyroidism on levothyroxine, allergic to penicillin (rash). Chief complaint: “My gums bleed when I brush, but I don’t have pain.” HPI: mild bleeding, no pain, no swelling. PMH: hypothyroidism, pregnancy (first trimester).
OObjective
Extraoral: normal. Intraoral: BOP 10 % of sites, PD ≤3 mm, no CAL, plaque index 20 %, no suppuration, no mobility, no furcation involvement. Radiographs: none taken.
AAssessment
Gingival health; plaque-induced gingivitis, Stage I, Grade A, supported by BOP 10 %, PD ≤3 mm, plaque 20 %, no attachment loss.
PPlan
Prophylaxis performed: scaling, polishing, OHI, fluoride varnish 5 % on all teeth. No anesthesia or drugs used. Patient advised to maintain oral hygiene, use soft-bristle brush, avoid trauma, and return for routine care.
29-year-old female, former smoker, NKDA, who presents with a chief complaint of a “big gum bump” on her upper left first molar; she reports the swelling has been present for several weeks and has not improved with home care.
OObjective
Extraoral exam is unremarkable. Intraoral examination shows BOP at 20 % of sites, probing depths of 4 mm around tooth #16, no recession, CAL of 4 mm, and a 3 mm thick hyperplastic gingival mass covering the buccal and palatal aspects; there is no suppuration, no tooth mobility, and no furcation involvement. Radiographs show no periapical pathology.
AAssessment
Diagnosis is medication-induced gingival hyperplasia affecting tooth #16, evidenced by the thick hyperplastic tissue, localized bleeding on probing, and preserved attachment levels.
PPlan
Gingivectomy of the hyperplastic tissue with curettage was performed under 2 % lidocaine with 1:100 000 epinephrine, 1.8 mL infiltration. Post-operative instructions included chlorhexidine 0.12 % rinses twice daily, avoidance of brushing the surgical site for 48 hours, and a return to clinic in 3 months for periodontal maintenance and reassessment of tissue response.
Gingival Hyperplasia
Gingival Hyperplasia, Tooth 16
SOAP note
SSubjective
19-year-old male, smoker 5 cigarettes/day, NKDA, reports “I have a big gum around my front tooth.” History: no systemic symptoms, no medications.
OObjective
Extraoral normal. Intraoral: tooth #7 shows probing depth 4 mm buccal and lingual, BOP 0%, CAL 0 mm, 1 mm hyperplastic gingival margin apical to CEJ, mobility Miller 0, no suppuration, plaque 15%, radiograph shows no bone loss, no furcation involvement.
AAssessment
Gingival hyperplasia, tooth #7, supported by 1 mm apical gingival margin and 4 mm probing depth with no attachment loss or bone loss.
PPlan
Debridement of hyperplastic tissue performed with a scalpel; oral hygiene instruction given; patient advised to reduce smoking; no drugs prescribed; next visit scheduled in 3 months for reassessment.
Gingival Hyperplasia, 4-Month Recall
SOAP note
SSubjective
62-year-old male, controlled hypertension on lisinopril, NKDA, CC: “Just here for my routine cleaning.” HPI: no pain, no bleeding, routine recall.
OObjective
Extraoral normal. Intraoral: tooth #16 buccal/lingual PD 3 mm, BOP 0 %, CAL 0 mm, gingival margin 0.5 mm apical to CEJ, 0.5 mm hyperplastic tissue, mobility Miller 0, no suppuration. Plaque score 10 %. Radiograph: no bone loss.
AAssessment
Gingival hyperplasia, tooth #16, supported by 0.5 mm hyperplastic tissue on #16 with normal PD, BOP, and CAL.
PPlan
Scaling of hyperplastic tissue performed; oral hygiene reinforced; antihypertensive medication reviewed; next recall scheduled in 3 months.
How to Document Pocket Depths and Bleeding on Probing
Pocket depths are measured at six sites per tooth, recorded in millimetres, and entered immediately during the exam. Bleeding on probing (BOP) is noted per site; the template allows a summary of BOP as a percentage of total sites or individual site flags. Record each depth and BOP in the same line to preserve contemporaneous data. If a measurement is entered later, label it “Late Entry – {date}” and add a single line through the original value with an initialed, dated correction; never erase. Integrate the data into the SOAP note by appending the pocket depth table to the Objective section, then reference the table in the Assessment (e.g., “Stage II periodontitis, 30% BOP”) and use the figures to guide the Plan (e.g., “SRP on quadrants 1–2, re-evaluate in 4 weeks”). The template’s built-in table aligns depths, BOP flags, and CAL calculations for quick review.
When to Refer to a Periodontist
Pocket depths exceeding 6 mm or clinical attachment loss >5 mm signal advanced periodontitis that warrants specialist input. Generalized disease—defined as ≥30 % of sites with PD ≥4 mm and CAL ≥3 mm—also indicates a need for a periodontist. Rapid progression, identified by a Grade C status or a sudden increase in pocket depth or attachment loss, requires referral. The template automatically flags these thresholds; when any are met, a referral note appears in the Plan section. Document the findings, state the referral, and schedule a follow-up appointment with the periodontist.
{visit_type_plan} – for prophylaxis: “full-mouth scaling, polishing, OHI”; for SRP: “quadrants 1–2, ultrasonic scaling, hand curettes, re-evaluation in 4 weeks”; for maintenance: “monitor PDs, reinforce OHI, schedule next recall in 3 months”.
{next_visit_interval} – 4 weeks after SRP, 3 months for stable maintenance, 6 months if BOP remains high.
{stage} {grade} – derived from pocket depths and BOP (e.g., “Stage II Grade A” or “Stage III Grade C”).
{additional_diagnosis} – include any comorbid periodontal findings such as “localized CAL loss 3–4 mm” or “generalized periodontitis, molar-incisor pattern”.
These examples show structure and wording only. Record what you actually found and did, and follow your practice’s documentation requirements.
Dr. Rahul Joshi is a Specialist Orthodontist with extensive clinical experience in orthodontics, dentofacial orthopaedics, and dental aesthetics. Holding a Master of Dental Surgery (MDS) in Orthodontics and Dentofacial Orthopaedics and a Bachelor of Dental Surgery (BDS) from Manipal Academy of Higher Education, he brings expertise in orthodontic treatment planning, teeth alignment, and Invisalign treatment. With professional experience across India and the Netherlands, Dr. Joshi combines clinical knowledge with practical experience in orthodontic care, dental aesthetics, and improving patients' oral health.
Master of Dental Surgery (MDS) in Orthodontics and Dentofacial Orthopaedics — Manipal Academy of Higher Education
Bachelor of Dental Surgery (BDS) — Manipal Academy of Higher Education
Stop retyping your templates
Save any template to TextOps once, then insert it anywhere on the web without retyping. Share it with your team so everyone uses the same wording.